

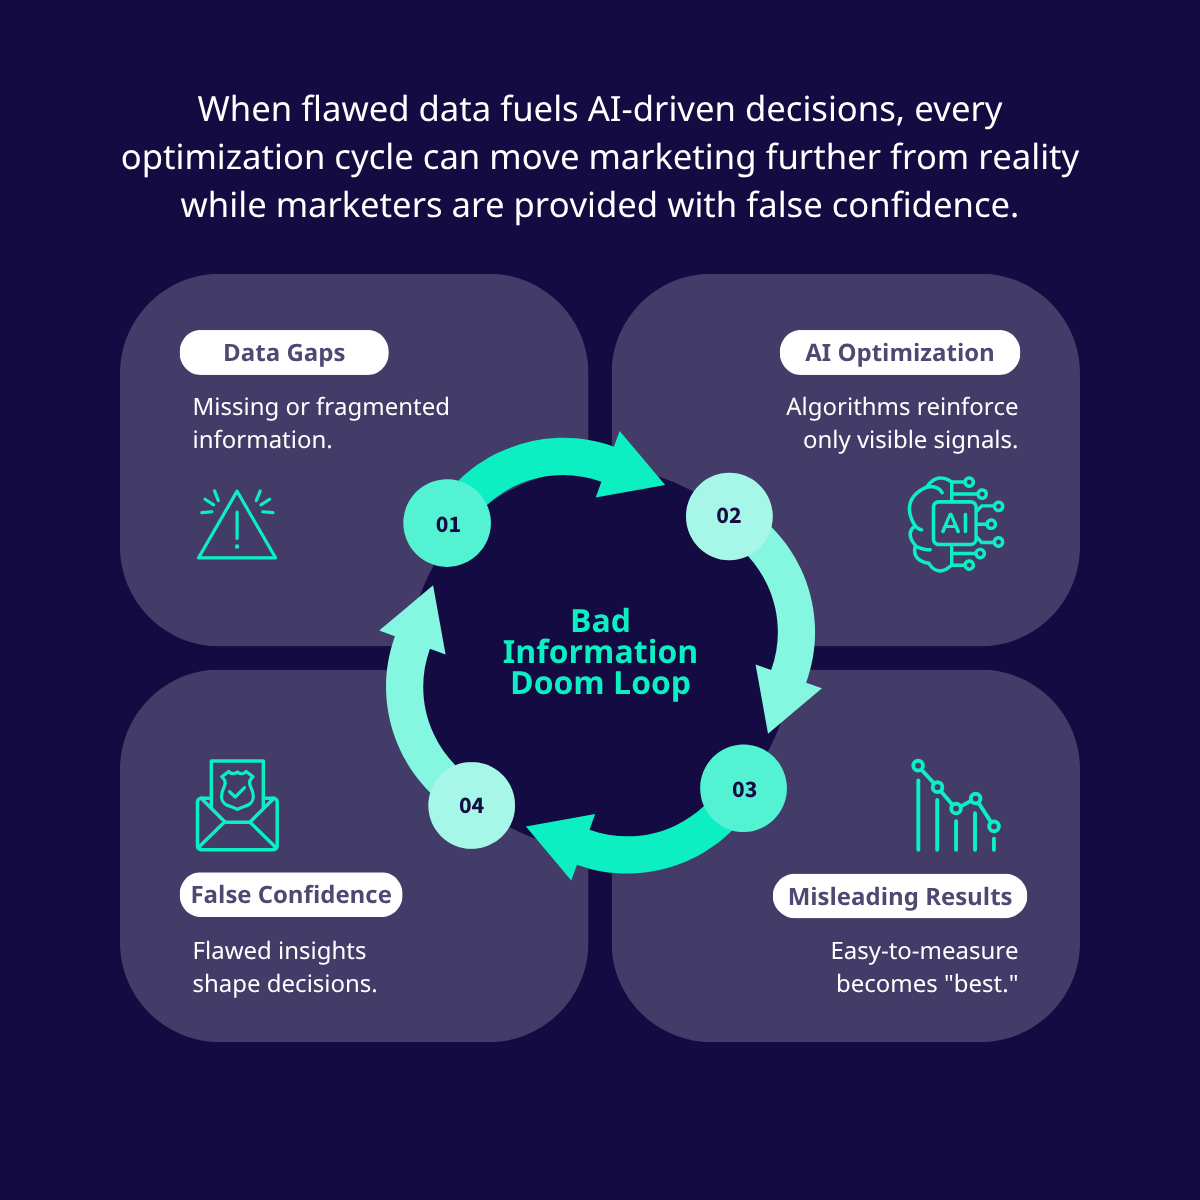
In the AI era, "garbage in, garbage out" is no longer a technical warning. It is a business reality.
AI can optimize campaigns, identify audiences and recommend where to invest the next marketing dollar faster and more effectively than ever before. What it cannot do is recognize when the underlying data is incomplete, outdated or inaccurate. It simply builds on the information it is given.
As AI becomes increasingly commoditized, most brands now have access to similar models, platforms and
Read More
From Members to Ecosystems: How Medical Societies Can Steward Specialty Data in the Age of AI

Medical societies hold one of the most valuable and underappreciated assets in healthcare today: specialty clinical data.
Through years of quality reporting, education, and clinical collaboration, many have developed longitudinal, clinically grounded registries that reflect real-world practice. As demand for real-world evidence grows and new analytical capabilities emerge, these datasets are becoming more valuable and increasingly sought after.
Medical societies now face a clear and
Read More
How Virtual Care and AI Unlock Outcomes-Based Autism Therapy

For years, autism therapy has forced healthcare purchasers into a false choice: expand access or control costs.
But as diagnoses in the U.S. have climbed to one in every 31 children, demand for care has outpaced the supply of Board Certified Behavior Analysts (BCBAs), the profession's most highly trained clinicians. Providers are responding by prescribing more therapy hours delivered by larger teams of lesser-trained clinicians, while payors continue to reimburse them for every additional
Read More
Healthcare AI Governance: Moving from Data-Sensitivity Tiers to Reversibility Controls in Agentic Systems

Ashok Benial is right. His argument in these pages last week — that most hospitals are buying AI faster than they can govern it, that "the tools go live while the guardrails are still on a slide deck" — is the most useful thing anyone has said about healthcare AI governance this quarter. His three controls are the correct ones: validate locally against your own population, monitor for drift after go-live, and fund the human review layer as a control system rather than overhead. Every health
Read More
Healthcare Doesn’t Need Forward Deployed Engineers. It Needs Forward Deployed Operators.

The forward deployed engineer model, embraced across enterprise technology, is built on a seductive assumption: that the gap between a technology's potential and its adoption is primarily a technical gap. A missing integration. A misconfigured workflow. A feature not yet built. Fix the code, and the organization will follow.
In most industries, that assumption is partially right. In healthcare, it is almost entirely wrong.
In part, healthcare organizations contribute to the problem
Read More
Healthcare AI ROI Should Be Measured by Work Completed, Not Tasks Automated

Healthcare executives are being asked to approve AI investments through dashboards that emphasize activity: messages drafted, calls summarized, records reviewed and minutes saved. Those numbers show that a system is being used. They do not show whether the work reached a useful conclusion.
That distinction is easy to miss because healthcare workflows are divided into small steps. A patient message can be drafted while the request remains unanswered. A clinical note can be generated but still
Read More
Healthcare’s Semantic AI Blind Spot: Why LLMs Cannot Replace Deterministic Data Infrastructure

Healthcare AI has reached an inflection point. AI is rapidly moving from isolated demonstrations to production systems embedded in clinical, operational, and research workflows. A new generation of AI applications is emerging to support nearly every aspect of healthcare delivery, operations, and research.
As organizations deploy these capabilities at scale, they are exposing an invisible semantic challenge that has quietly existed for decades. Clinical information is translated
Read More
Healthcare AI’s Decision Intelligence Mandate: Turning Predictive Analytics into Timely Clinical and Operational Action

For years, healthcare leaders have asked if artificial intelligence can predict what will happen next, such as who might be readmitted, which patients could get worse, where resources are needed, and which interventions could help. Today, we can answer many of these questions, but a tougher question is what a healthcare organization should actually do with these predictions.
This is where much of healthcare AI still falls short.
The industry has invested heavily in electronic health
Read More
Why Calibrated Uncertainty and Deliberate Abstention Drive True Clinical AI Adoption

Most teams building AI systems treat confidence as a solved problem. The model produces a probability, the interface displays it, and the reliability requirement gets checked off. Within weeks, the number becomes furniture. Anyone who has watched a clinician work through a queue of suggested codes, each stamped with a confidence percentage, knows the pattern: when the scores cluster near the top of the range, a 92 gives the reviewer little more reason to act than an 89, and they fall back on
Read More
Biohacking’s Gender Problem: Why Women’s Health Protocols Require Dedicated Research and Clinical Variables

Ask most people to describe a biohacker, and you'll likely hear about a man in his thirties with a cold plunge, a spreadsheet, and a strong opinion about seed oils. Ask a fifty-year-old woman whether she tracks her sleep, times her protein intake, lifts weights three times a week, and reads her own lab results before her doctor does, and she'll say yes. She just won't call it biohacking. The habits are the same. The label and who gets credit for it are something else entirely.
Start with the
Read More
